13
min read
Building a Business Case for AI Documentation in European GP Practices
Learn how to construct a rigorous business case for AI-assisted documentation in European primary care, covering ROI, compliance, and stakeholder perspectives
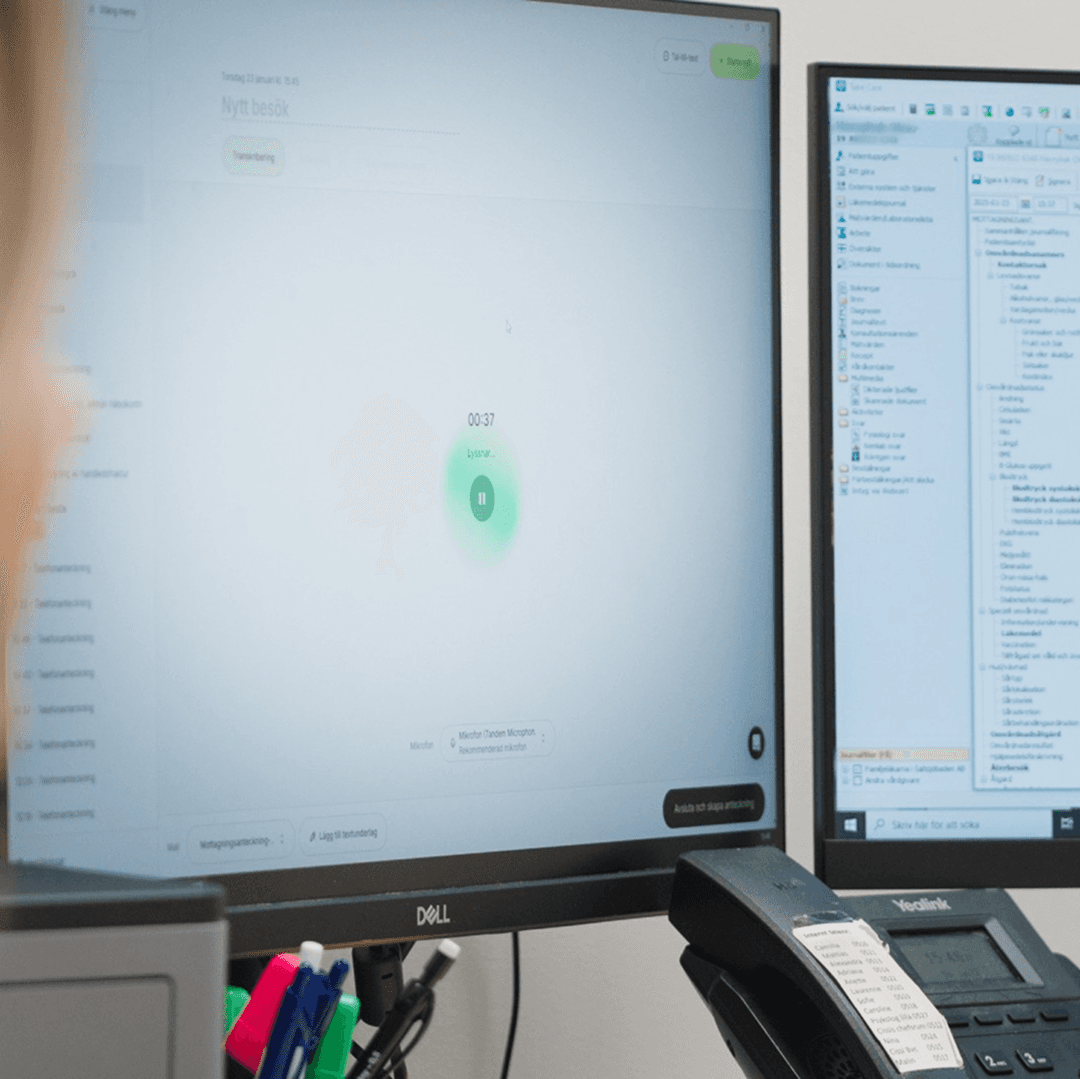
Building a business case for AI-assisted documentation in European GP practices means satisfying four distinct audiences: clinical leads, practice managers, information governance officers, and GPs. Each evaluates the proposition through a different lens. This guide sets out how to address all four rigorously.
Why European GP practices are reconsidering documentation tools now
Several converging pressures have brought AI-assisted documentation into serious consideration across European primary care. A 2025 European Parliament briefing confirmed that the EU faces a shortage of 1.2 million doctors, nurses, and midwives, driven primarily by an ageing population and workforce attrition. Administrative burden is a leading cause of GP burnout across France, Germany, the Netherlands, Sweden, Switzerland, and the UK, with documentation alone estimated to consume around three hours of a physician's working day.
The regulatory landscape has also shifted materially. The EU Artificial Intelligence Act entered into force in August 2024, the European Health Data Space regulation passed in 2025, and the European Commission has identified four categories of challenges to clinical AI deployment: technological, legal and regulatory, organisational, and social. A sound business case needs to address all four. Meanwhile, the first large-scale European clinical evidence on AI scribes has started to emerge, giving procurement teams data from comparable healthcare systems rather than having to rely solely on literature from the United States.
What the business case must prove
Before exploring what an AI medical scribe is and how it works, it helps to be clear about what a credible internal proposal actually needs to demonstrate. Decision-makers need answers to four questions: Does the tool save measurable time per consultation, per clinician, per week? Does it reduce clinical risk through better documentation quality? Does it comply with EU law, including the General Data Protection Regulation (GDPR), the Medical Device Regulation (MDR), and data residency requirements? And does it deliver a return on investment within a realistic timeframe? Any business case that cannot answer all four is unlikely to pass governance approval in a European clinical setting.
Quantifying the documentation burden and its real costs
Before any return on investment calculation is possible, a practice needs an accurate baseline of its current documentation load. The key metrics to capture are: average time per consultation spent on notes (including time spent finishing notes after the appointment), total weekly admin hours per clinician broken down by task type, and indirect costs such as appointment backlogs, overtime, and locum expenditure. Self-reported time estimates alone are often unreliable. A 2026 physician survey across primary care clinics confirmed this, so a two-to-four-week time-in-motion study, in which a representative sample of GPs log documentation time per consultation, produces the defensible baseline figure the return on investment model needs.
The business case becomes significantly stronger when it moves beyond time-on-task to the broader organisational costs of the paperwork load. Replacing a GP carries substantial costs in advertising, onboarding, and temporary cover, costs that rarely show up in standard financial reporting. A 2025 Lancet Regional Health Europe paper on workforce psychological distress identifies high workloads and organisational factors as the primary contributors to burnout and intention to leave across European health systems. When note-writing overruns eat into time that could otherwise support patient-facing activity, effective appointment capacity falls directly. Rushed or incomplete records create downstream risk through missed clinical codes, delayed referrals, and incomplete patient summaries, with both clinical and medico-legal implications. Research on ambient AI documentation and cognitive load has also found that reducing the writing burden during the consultation supports more patient-centred care.
How AI-assisted documentation works and what the evidence shows
AI-assisted documentation in a GP consultation works through three sequential steps. Ambient voice technology captures the spoken conversation in real time. The system then processes the transcript and generates a structured clinical note, formatted to match the relevant template or medical record system field. Finally, the clinician reviews the draft, edits as necessary, and approves it before it enters the patient record.
The strongest European evidence to date comes from a study conducted with 1,295 clinicians across Swedish primary and secondary care settings. The first large-scale European clinical study on AI scribes found a 29 per cent reduction in documentation time, from 6.69 minutes to 4.71 minutes per note, across more than 375,000 clinical notes. That figure carries particular weight for European procurement teams because it comes from a comparable regulatory and workflow environment. A comparative study of AI scribes versus human documentation in simulated general practice consultations found that note quality was comparable between the two. The mechanism behind the time saving is straightforward: separating active listening from active typing removes the cognitive penalty of doing both at once, which is what drives both errors and post-consultation note completion time.
Building the ROI model
A practical return on investment model doesn't require financial modelling expertise. If average documentation time per consultation falls from 6.5 minutes to 4.5 minutes, that's 2 minutes saved per consultation. For a GP seeing 25 patients a day, that recovers 50 minutes daily, roughly four hours per week. Across a practice of five GPs, that's 20 hours per week, expressible either as additional appointment capacity or as an equivalent reduction in overtime or locum hours.
Divide the annualised licensing cost, typically a per-clinician subscription, by the quantified weekly gain to get a payback period. Where baseline data captures overtime costs, locum expenditure, or the cost of managing appointment backlogs, include these as avoided costs rather than direct savings. This reflects the true cost of the writing load more accurately and strengthens the financial argument. For context: ambient clinical documentation generated $600 million in 2025, representing 2.4 times year-on-year growth, with thin margins and staff shortages identified as the primary drivers of adoption. That suggests the ROI case is landing in practice, not just on paper.
Compliance as a central pillar: GDPR, MDR, and data residency
In European clinical settings, regulatory compliance is a procurement prerequisite. A tool that cannot demonstrate regulatory alignment will not get through governance approval, regardless of its clinical performance. EU data protection and health AI policy creates four specific requirements that procurement teams must obtain in writing from any vendor:
A GDPR-compliant Data Processing Agreement (DPA) covering special category health data under Article 9, specifying the lawful basis for processing, data subject rights, and processor obligations
Explicit confirmation that patient data is processed and stored within the EU or European Economic Area (EEA), with disclosure of any third-party sub-processors located outside the EU
Written confirmation of MDR classification status. Where a tool includes any clinical decision support or produces outputs that influence clinical decisions, it may require registration as a medical device under EU MDR.
ISO 27001 certification, which NHS and European health system procurement teams increasingly expect as a baseline information security standard
GP practices are particularly exposed here. A scoping review of security and privacy challenges in digital health technologies in primary care identifies decentralised and resource-limited settings as especially vulnerable to data privacy risks, which is directly relevant to practices that may not have dedicated information governance staff. Procurement teams should request all four documents from any vendor under consideration before the evaluation proceeds further.
Framing the case for each stakeholder
The same evidence base needs to be presented differently depending on who's in the room.
Clinical leads are primarily concerned with workflow fit and clinical quality: peer-reviewed accuracy data from comparable European primary care settings, and confirmation that the clinician retains full editorial control over every note. Practice managers focus on cost and operational impact. For this audience, framing time saved as additional appointment capacity is often more persuasive than framing it as reduced stress, so lead with the ROI model, payback period, and reduction in overtime or locum costs. IT and information governance leads need written documentation on GDPR compliance, data residency, ISO 27001 certification, MDR classification, and medical record system integration. Verbal assurances are insufficient.
GPs are often the most sceptical audience, and that scepticism deserves to be taken seriously rather than managed. Research on how AI automation of administrative tasks affects healthcare professionals' work in Swedish primary care highlights the importance of addressing workflow disruption concerns directly and involving clinicians in pilot design rather than imposing adoption from the top down. Peer evidence, meaning data from GPs in comparable settings who report reduced cognitive load and less time finishing notes after appointments, tends to land better than vendor claims. The business case should lead with it when presenting to clinical staff.
Running a pilot to generate locally relevant evidence
A structured pilot converts the business case from a theoretical projection into a locally evidenced proposal. Three to five GPs over four to eight weeks is sufficient. The group should span a range of consultation complexity, digital confidence levels, and patient demographics, and should include at least one clinician who's sceptical of the tool, because that strengthens the credibility of positive results.
Define success metrics before the pilot begins, so results can't be attributed to selective reporting after the fact. Relevant metrics include average time per note (baseline versus pilot), post-consultation note completion rate and time to completion, clinician-reported cognitive load using a validated instrument such as the NASA Task Load Index, clinician satisfaction with note quality, and any documentation errors or corrections required. The first two weeks typically involve a learning curve; weeks three to eight reflect steady-state performance. Record results in a format that maps directly to the ROI model and compliance assessment, so pilot findings feed into the formal business case without requiring additional analysis.
For the broader evidence base, prioritise peer-reviewed literature from comparable primary care contexts. The Lancet Primary Care review of AI in primary care and the European General Practice Research Network (EGPRN) keynote paper on AI for GPs are the strongest reference points for a European audience. A prospective evaluation of a bilingual Arabic-English ambient AI scribe also demonstrated reduced documentation burden in real-world implementation, which is useful for European practices operating across languages.
Common objections and how to address them
"The AI might make clinical errors in the notes." Comparative evidence from simulated GP consultations shows AI-generated notes are comparable in quality to human-generated documentation. The current standard, a clinician typing while simultaneously consulting, carries its own error risk, and AI-assisted documentation with mandatory clinician review adds an explicit quality gate that many manual workflows lack.
"GPs won't adopt it." Adoption concerns are best addressed through co-design rather than top-down implementation. Piloting with volunteers, sharing results transparently, and allowing opt-in adoption reduces resistance.
"We're not sure about data security." Request the vendor's DPA, ISO 27001 certificate, data residency confirmation, and MDR classification status in writing. If the vendor cannot supply these, the concern is substantiated and the tool should not proceed to procurement.
"It won't integrate with our medical record system." Ask specifically: Does the tool integrate natively with the practice's medical record system, or does it require copy-pasting? Does it support the clinical coding standards used in the national system, such as SNOMED CT, ICD-10/11, or Read codes? What's the integration implementation timeline and cost?
What a complete business case document should contain
A complete submission should cover eight areas. An executive summary gives decision-makers a one-page overview of the problem, proposed solution, key financials, and recommended decision. The current state analysis sets out baseline documentation time data, clinician hours lost to admin, and any available data on burnout indicators or staff turnover. A proposed solution overview describes clearly and without promotional language how the tool works, what it does and doesn't do, and which clinical workflows it affects.
The compliance assessment presents written confirmation of GDPR alignment, data residency, MDR classification, and ISO 27001 status, with copies of relevant certificates. The ROI model contains the full financial calculation with stated assumptions, a sensitivity analysis for lower-than-expected adoption, and a projected payback period. Pilot findings then map structured results from the internal trial against the pre-defined success metrics. An implementation plan covers training requirements, medical record system integration steps, and a phased rollout timeline. Finally, a risk register identifies adoption failure, integration issues, and data security incidents as the primary risks, with mitigations and assigned ownership for each.
Choosing the right vendor for a European practice
Vendor selection in a European primary care context requires criteria that go beyond clinical accuracy claims. Ask for published or independently validated accuracy data, specifically word error rates for speech-to-text and data on clinical note completeness in primary care consultations, not marketing materials. Confirm the exact depth of integration with the specific medical record system in use, and ask for a technical integration specification document rather than a generic compatibility claim. European practices frequently involve clinicians and patients whose first language isn't English, so ask for specific evidence of performance in the languages and dialects relevant to your setting.
On compliance, the minimum requirements are ISO 27001 certification, a GDPR-compliant DPA, EU data residency confirmation, and written MDR classification status. Favour short initial contract terms of six to twelve months with renewal options. This lets practices exit if adoption or performance targets aren't met. Make sure the vendor can provide clear escalation paths for technical issues that come up during clinical hours.
Ask for references from GP practices or primary care organisations in the EU or EEA specifically. The EGPRN's analysis makes the point plainly: AI tools designed for GP needs within European health systems, including fragmented care settings and high-demand primary care contexts, are likely to deliver meaningfully different outcomes than tools built primarily for US hospital environments. Reference cases from comparable settings carry more evidential weight than vendor claims, and vendor selection criteria should reflect that.
Frequently asked questions
▶ What does a business case for AI-assisted documentation need to prove?
Four questions must be answered: does the tool save measurable time, does it improve documentation quality, does it meet EU legal requirements, and does it pay back within a realistic period? Governance approval in European clinical settings depends on satisfying all four. A gap in any one of them is typically enough to stall the process.
▶ How does AI-assisted documentation actually work in a GP consultation?
Ambient voice technology captures the consultation in real time, the system generates a structured draft note, and the clinician reviews and approves it before it enters the patient record. The key practical point: the clinician's approval step is what makes the output a clinical record, so the tool cannot write to the record autonomously.
▶ What time savings does the evidence show for AI documentation tools in European primary care?
The Swedish large-scale study (1,295 clinicians, 375,000 notes) found a 29 per cent reduction, from 6.69 to 4.71 minutes per note. For procurement purposes, the more useful figure is cumulative: across a five-GP practice, that saving compounds to roughly 20 hours per week, which is the number that drives the ROI calculation.
▶ How do you build an ROI model for a GP practice considering this technology?
The model only holds up if the baseline is measured, not estimated. Run a two-to-four-week time-in-motion study before building any figures, because self-reported documentation times are consistently unreliable. Once you have a defensible baseline, divide the annualised licence cost by the weekly hours recovered to get a payback period the finance team will accept.
▶ What are the EU regulatory requirements a vendor must meet before procurement?
Request four documents in writing before evaluation proceeds: a GDPR-compliant Data Processing Agreement covering Article 9 health data, EU or EEA data residency confirmation, MDR classification status, and ISO 27001 certification. If a vendor cannot supply all four, that is the answer to the compliance question.
▶ Are AI-generated clinical notes as accurate as manually written ones?
A comparative study in simulated GP consultations found quality was comparable between AI-generated and human-generated notes. The more useful framing for a governance audience: mandatory clinician review before any note enters the record is an explicit quality gate that many current manual workflows do not have.
▶ How should a GP practice structure a pilot before committing to full adoption?
Include at least one sceptical clinician in the pilot group. Positive results from a cohort that included a sceptic carry more weight with governance committees than results from volunteers who were already enthusiastic. Set success metrics before the pilot starts so the findings cannot be attributed to selective reporting after the fact.
▶ Why does documentation burden matter beyond the time it takes?
The financial case extends well beyond overtime. GP replacement costs, covering advertising, onboarding, and locum cover, rarely appear in standard reporting but are substantial. Incomplete notes also carry medico-legal exposure through missed codes and delayed referrals. These costs are real whether or not they show up in the budget line a practice manager typically reviews.
▶ How should the business case be framed for different stakeholders in a GP practice?
The evidence base is the same for every audience, but the entry point differs. Lead with capacity and cost for practice managers, compliance documents for IT and governance leads, and peer evidence for GPs. The order in which you present the same facts determines whether each audience engages or disengages before reaching the conclusion.
▶ What should you look for when choosing an AI documentation vendor for a European practice?
Ask for references from GP practices in the EU or EEA, and ask specifically about performance in the languages your clinicians and patients use. Request a technical integration specification for your actual medical record system rather than a generic compatibility claim. Favour contract terms of six to twelve months initially so the practice can exit if adoption targets are not met.